Consider this teaching scenario. A patient remains hypotensive after initial resuscitation. A passive leg raise increases stroke volume. The instinct is understandable: they are fluid responsive, so give more fluid.
But their oxygen requirement is climbing, and ultrasound suggests congestion. Now the question changes: will that increase in flow be worth the physiological cost?
Fluid responsiveness predicts a haemodynamic response. Fluid tolerance asks whether the patient can accommodate the volume without harmful congestion. The two can coexist, but one does not establish the other. [1]
The why: flow and pressure can rise together
The Frank–Starling mechanism explains why increased ventricular filling can increase stroke volume. A positive responsiveness test tells us that the heart can still produce more forward flow when preload increases. It does not prove that filling pressures are safe, that the lungs will tolerate more fluid, or that tissue perfusion needs that extra flow. [1]
A stiff ventricle may require a substantial rise in filling pressure for a modest increase in output. Higher pulmonary venous pressure can promote lung edema. On the right side, rising venous pressure can reduce the pressure gradient driving blood through organs. Kidney perfusion depends partly on blood being able to leave, as well as arrive. In sepsis, a dysfunctional endothelial barrier compounds the risk of tissue edema. [1,2]
That is how a bolus can improve a measured stroke volume while adding physiological harm. More flow is a potential benefit; more congestion is a potential cost.
Responsiveness is therefore one part of a fluid decision, alongside an indication to improve perfusion and an assessment of tolerance.
The POCUS lesson: ask three questions
1. Does this patient need better perfusion?
Assess capillary refill, mental status, urine output and the clinical trajectory alongside arterial pressure and lactate. Hypotension alone does not identify the mechanism of shock or prove a need for more volume. [3]
2. Will increasing preload increase flow?
When feasible and appropriate, use passive leg raising with a prompt measurement of stroke volume or cardiac output. With echocardiography, serial left ventricular outflow tract velocity time integral (LVOT VTI) can track the response. Measure before, during and after the manoeuvre, maintaining the same acquisition technique. Blood pressure alone is an unreliable substitute. [4]
Why? Passive leg raising temporarily redistributes the patient’s own blood, allowing a reversible preload test without committing to an intravenous bolus. [4]
3. What is the cost of adding volume?
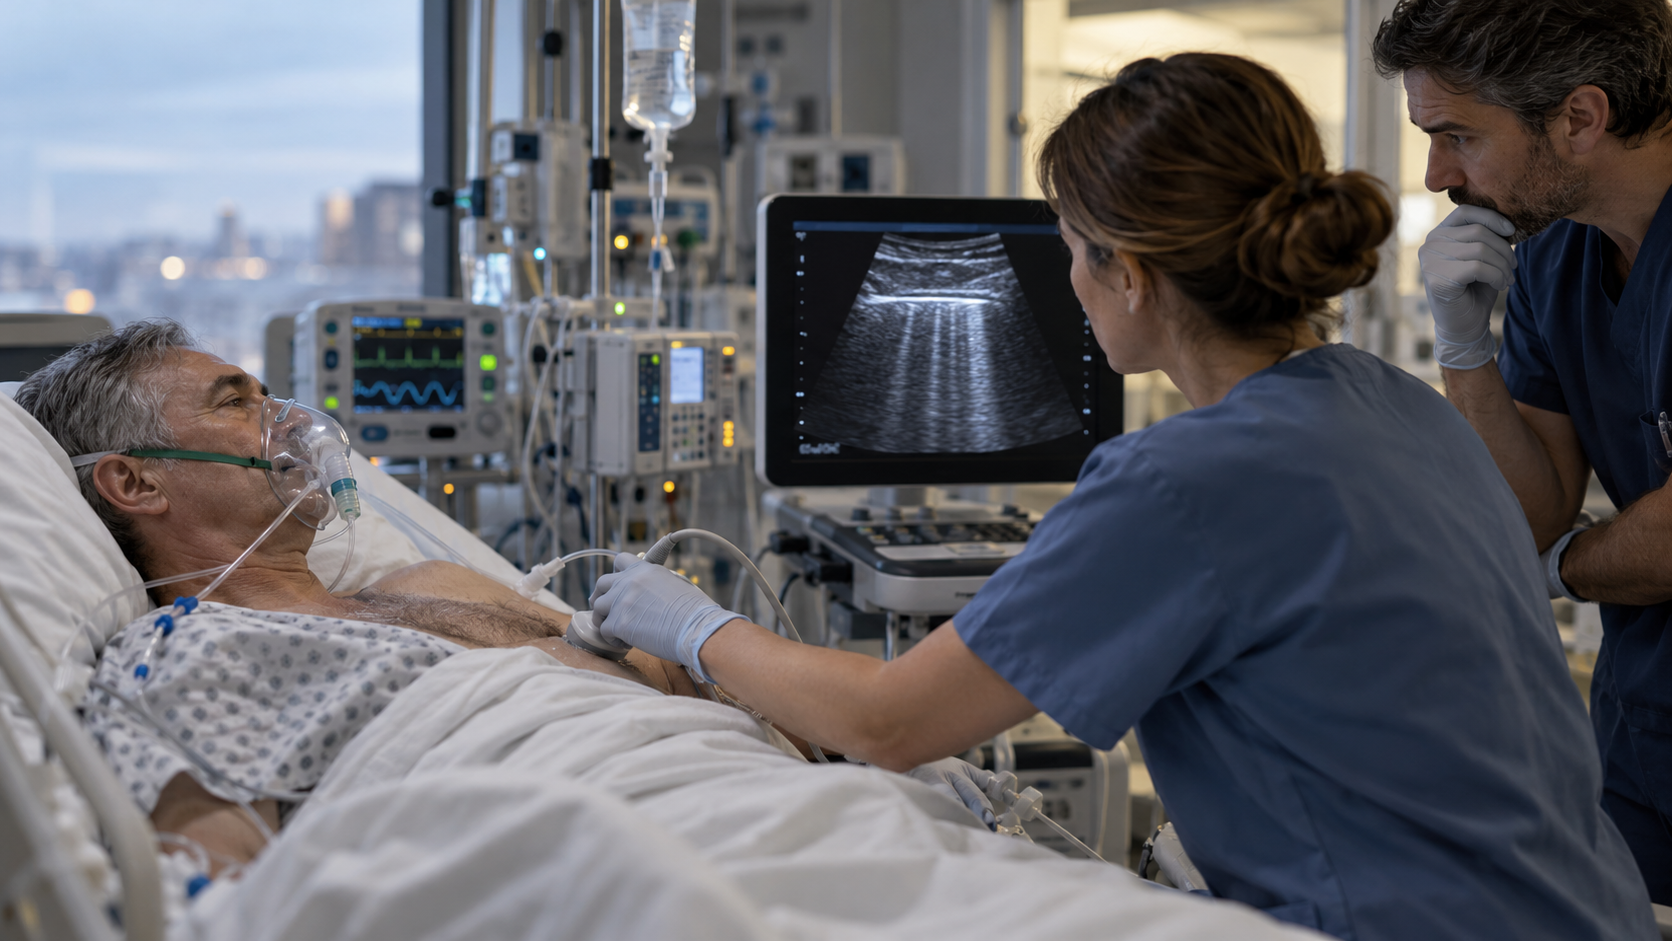
Combine ventricular assessment with lung ultrasound and, where expertise permits, venous Doppler. VExUS integrates inferior vena cava findings with hepatic, portal and intrarenal venous waveforms to assess systemic venous congestion. An isolated IVC image does not answer all three questions. [1,2]
New or increasing B-lines, interpreted with worsening oxygenation, may signal declining pulmonary tolerance. B-lines also occur in ARDS, pneumonia and fibrosis, so their distribution, accompanying findings and trend matter. Neither B-lines nor VExUS should become an automatic treatment command. [2,5]
What the new trial adds
A multicentre trial published in Critical Care on 26 September 2026 tested fluid-intolerance signals in ventilated adults with septic shock who remained fluid responsive and hypoperfused, and were at increased risk of fluid-related harm. Lung ultrasound, VExUS, estimated cardiac filling pressure and central venous pressure informed limits on further boluses. [6]
Among 35 analysed patients, median protocol bolus volume over six hours was 250 mL with intolerance-guided care versus 650 mL with standard care. Oxygenation changes favoured the intervention; changes in lactate and capillary refill did not differ. Total fluid exposure, including fluid before randomisation, was similar. [6]
The trial stopped before its planned sample size. It provides a preliminary physiological signal, not proof of improved survival, established safety equivalence, or a validated protocol for all shock patients. [6]
Treat the physiology, then reassess
After initial resuscitation, persistent shock calls for repeated assessment of perfusion, responsiveness and the cause of shock. The 2025 ESICM guidance supports dynamic testing and echocardiography rather than reliance on static preload markers. [3]
Our practical interpretation: if more volume is likely to help and tolerance appears adequate, give a measured challenge and reassess. If congestion is worsening, reconsider the bolus and address the underlying physiology, including vasodilation or ventricular dysfunction. [1,3]
Before the next bolus, ask: what benefit am I seeking, and what harm am I watching for?
AGC Med. Where science meets humanity.
References
1. Kenny JES, Prager R, Rola P, et al. Unifying Fluid Responsiveness and Tolerance With Physiology: A Dynamic Interpretation of the Diamond–Forrester Classification. Critical Care Explorations. 2023;5(12):e1022. Read source
2. Beaubien-Souligny W, Rola P, Haycock K, et al. Quantifying systemic congestion with Point-Of-Care ultrasound: development of the venous excess ultrasound grading system. The Ultrasound Journal. 2020;12:16. Read source
3. Monnet X, Messina A, Greco M, et al. ESICM guidelines on circulatory shock and hemodynamic monitoring 2025. Intensive Care Medicine. 2025;51:1971–2012. Read source
4. Monnet X, Teboul JL. Passive leg raising: five rules, not a drop of fluid! Critical Care. 2015;19:18. Read source
5. European Association of Cardiovascular Imaging. Lung ultrasound in acute and chronic heart failure: a clinical consensus statement. European Heart Journal – Cardiovascular Imaging. 2023;24(12):1569. Read source
6. Melo P, Amthauer M, Ferri G, et al. Fluid-intolerance signals as bedside safety limits during early septic shock resuscitation: a multicenter randomized trial. Critical Care. Published 26 September 2026; advance article. Read source